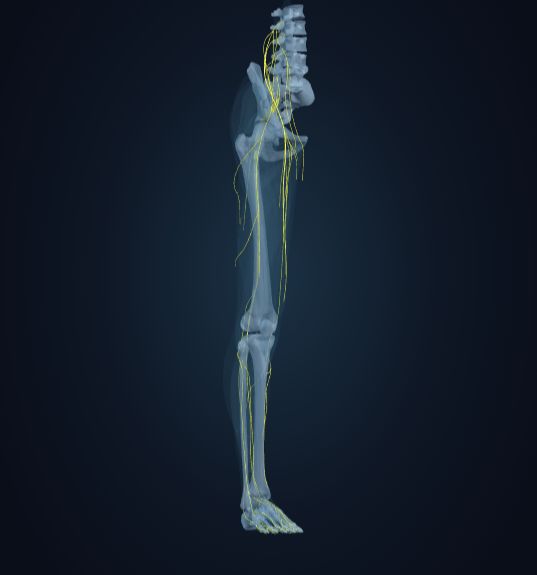
A nerve needs to glide as the body moves. A position, external pressure or muscle contraction can sometimes increase stress along its course. Understanding where, when and how symptoms occur helps guide assessment.
Right lower limb. Educational transparency keeps nerves visible through tissues. Z-Anatomy / BodyParts3D.
THE PRINCIPLE
Movement can reveal an entrapment.
“Dynamic” describes entrapment affected by movement or position. Symptoms may be intermittent despite a reassuring resting examination. Some compressions are nevertheless persistent and only aggravated by exercise.
01
Sensation
Burning, tingling, electric pain or numbness.
02
Strength
Weakness depends on the nerve and injury level. Some nerves are purely sensory.
03
Context
A scar, injury or neuroma is not necessarily dynamic entrapment.
/01 — EXPLORE BY REGION
Hip & thighDifferent nerves, sometimes overlapping symptoms.
Right lower limb. Educational transparency keeps nerves visible through tissues. Numbers link to possible release sites. Z-Anatomy / BodyParts3D.
These landmarks help explain the anatomy. Pain location alone cannot establish a diagnosis.
Sciatic nerve · deep gluteal region
In the buttock and behind the thigh, muscular or fibrous structures may cause entrapment in the deep gluteal space.
Possible symptoms
Buttock pain radiating into the thigh or leg, sometimes affected by sitting or hip movement.
Keep in mind
A lumbar cause must be considered. Not every sciatic pain is piriformis syndrome.
Lateral femoral cutaneous nerve
Near the inguinal ligament; a tight belt or clothing may contribute to meralgia paraesthetica.
Possible symptoms
Burning or numbness over the anterolateral thigh.
Keep in mind
This nerve is sensory: an isolated lesion does not cause weakness.
Femoral & obturator nerves
The femoral nerve supplies the quadriceps; the obturator nerve supplies several thigh adductors.
Possible symptoms
Weak knee extension, or medial thigh pain with adductor weakness, depending on the nerve.
Keep in mind
These conditions are less common. Weakness requires investigation for proximal injury, haematoma or other causes rather than assuming exercise-related entrapment.
/02 — EXPLORE BY REGION
Knee & lower legSaphenous and common fibular: different nerves.
Right lower limb. Educational transparency keeps nerves visible through tissues. Numbers link to possible release sites. Z-Anatomy / BodyParts3D.
These landmarks help explain the anatomy. Pain location alone cannot establish a diagnosis.
Medial & lateral plantar nerves
Tibial branches reaching the sole through fibrous passages including those beneath abductor hallucis.
Possible symptoms
Sole or toe sensory symptoms; the medial branch may be irritated in runners.
Keep in mind
Distal symptoms are not always explained by the tunnel behind the malleolus. Different causes may coexist.
Baxter’s nerve
The first branch of the lateral plantar nerve, implicated in some heel pain presentations.
Possible symptoms
Heel pain that may resemble plantar fasciopathy.
Keep in mind
Location alone is insufficient. Examination and, when appropriate, imaging help assess the possibilities.
Digital nerves · Morton’s neuroma
An interdigital nerve in the forefoot may become painful, often in the third interspace.
Possible symptoms
Burning, electric pain or a pebble sensation beneath the forefoot, sometimes affected by footwear.
Keep in mind
This “neuroma” is not an ordinary nerve tumour. Assessment and treatment are specific to this condition.
FROM SYMPTOM TO DIAGNOSIS
Connect the findings. No single test tells the whole story.
01
Describe
Pain distribution, time to onset, provoking position and recovery time.
02
Examine
Sensation, strength, reflexes, gait, joints, spine and circulation. A single provocative test is not enough.
03
Investigate
According to the suspected cause: electrodiagnostic testing, possibly dynamic ultrasound, MRI or other targeted investigations.
04
Bring findings together
Symptoms, the suspected site and findings should be consistent before treatment is chosen.
Electrodiagnostics: location and severity+
Nerve conduction studies and needle EMG assess nerves and selected muscles. They can help distinguish a peripheral lesion from a more proximal cause. Normal findings do not exclude every intermittent or small-branch lesion, but do not prove “hidden” entrapment.
Ultrasound & MRI: looking for a cause+
Imaging may assess nerve calibre, scarring, a cyst, a mass or muscle changes. Dynamic ultrasound can examine certain relationships during movement. An abnormal image must be interpreted in the clinical context.
Targeted block: supporting information+
A local anaesthetic injection performed by a professional may help localise pain in selected cases. Temporary relief does not guarantee surgical success.
AN INDIVIDUAL STRATEGY
Treat the cause. Not just the symptom.
01 / Reduce pressure
Adapt activity thoughtfully
Review footwear, equipment, pressure points and provoking movements. Rehabilitation and pain treatment are individualised. Avoid forceful stretching of an irritated nerve.
02 / Monitor progress
Track meaningful changes
Monitor walking tolerance, pain, sensation and strength. New or progressive weakness requires prompt reassessment. An ankle-foot orthosis may be prescribed to make walking safer.
03 / Consider a procedure
A clearly defined indication
Decompression may be considered for adequately documented, disabling entrapment despite appropriate care. A compressive mass or progressive deficit may change the priorities.
Decompression, neurolysis, neurectomy: what is the difference?+
Decompression opens a restrictive passage; neurolysis frees a nerve from surrounding restrictive tissues. Neurectomy divides or removes a nerve segment and may cause numbness or a new painful neuroma. These procedures are not interchangeable.
SIGNS THAT NEED ATTENTION
New weakness? Do not wait.
New or progressive weakness or foot drop, particularly after injury or surgery, needs prompt medical assessment.
In France, call 15 or 112 for a suddenly cold, pale foot, sudden severe pain with a tense leg, or back symptoms associated with bladder or bowel dysfunction or saddle numbness.
YOUR QUESTIONS
Clear answers, without shortcuts.
Are SPE and common fibular the same nerve?+
Yes. SPE is an older French abbreviation for the common fibular nerve, also called the common peroneal nerve.
Does a normal resting examination rule it out?+
It is part of the assessment, but may not capture an exercise-related problem. A clinician may use an appropriate movement assessment without deliberately provoking severe pain or weakness.
Is all exercise-related pain caused by nerves?+
No. Exertional compartment syndrome, tendon injury, stress fracture, vascular disease or a lumbar cause may produce similar symptoms. The appropriate investigations differ.
Does surgery mean a quick return to sport?+
There is no universal timeline. Return depends on the nerve, cause, injury and procedure. Releasing a nerve does not guarantee complete recovery of existing nerve damage.
Prepare for your consultation.
Note the exact area, triggering movement, time to onset and duration of symptoms. Mention any weakness, previous surgery or injury. Bring existing reports and images. Do not deliberately provoke weakness to demonstrate it.
Rigoard P (dir.). Atlas of Anatomy of the Peripheral Nerves: The Nerves of the Limbs – Expert Edition. Springer, 2020. DOI.
Boyd KU, Brown JM. Injury and Compression Neuropathy in the Lower Extremity. In: Mackinnon SE (dir.). Nerve Surgery. Thieme, 2015, chap. 13, p. 338–390.
Anatomical 3D models: Z-Anatomy (Gauthier Kervyn and contributors), derived from BodyParts3D (Kousaku Okubo, Database Center for Life Science). Right lower limb selection, framing, colours and transparency adapted. Educational views do not show all anatomical variations and cannot guide a procedure. No book figure or operative photograph is reproduced. Surgical case series do not promise an individual outcome.